A randomized, double-blind, placebo-controlled trial of N-acetylcysteine as an adjuvant treatment for alcohol use disorder
Abstract
Objective: We assessed the effect of N-acetylcysteine, as an adjuvant treatment, on treatment adherence (primary outcome) according to peripheral biomarkers and clinical improvement (secondary outcomes) in patients with alcohol use disorder.
Methods: A 9-week randomized, double-blind, placebo-controlled clinical trial was conducted on 53 (n = 25 N-acetylcysteine, n = 28 placebo) inpatients with alcohol use disorder. Neuropeptide Y, oxidative stress and inflammatory biomarkers, and hepatic parameters were analyzed at 3 time points.
Results: Seventeen (60.7%) patients in the placebo group and 16 (64%) patients in the N-acetylcysteine group completed the trial. Hepatic biomarker levels changed significantly over time (p < 0.001). Oxidized glutathione levels at admission were lower in the N-acetylcysteine group (ppairwise = 0.043). By the end of the study, both groups had similar oxidized glutathione levels (p = 0.868), and oxidized glutathione levels were lower in the placebo group. At the end of the intervention, superoxide dismutase activity had decreased and neuropeptide Y levels had increased in the N-acetylcysteine group. Both groups showed similar mean time to relapse, treatment adherence, and clinical improvement.
Conclusions: Our findings reinforce the effects of alcohol on oxidative stress and neuropeptide Y parameters. However, our sample size may limit the generalizability of the results, especially for clinical outcomes. Future randomized clinical trials including patients with less severe alcohol use disorder and longer follow-up may be needed to determine whether N-acetylcysteine could help reduce the mental health burden of this disorder.
Clinical Trial Registration: NCT03018236.
Alcohol; addiction; substance use disorder; N-acetylcysteine; clinical trial
Introduction
Substance use disorders (SUDs) present a wide range of cognitive, behavioral, and physiological symptoms. Individuals with SUD continue to use substances despite many adverse consequences.1 The worldwide prevalence of SUD is high, with approximately 1,358 cases per 100,000 individuals for alcohol use disorder (AUD) and 844 cases per 100,000 for other drug use disorders. Moreover, AUD accounts for 220 per 100,000 disability-adjusted life years,2 which is a measure used in Global Burden of Disease studies that combines years of life lost due to premature mortality with years of life lost due to disability.3 Thus, AUD ranks 20th among the most disabling health conditions in people aged 25-49.4
AUD is a complex clinical and etiological phenomenon, and multiple neurobiological pathways and social environments are associated with the disorder. By refining our conceptualization of AUD and identifying key factors that contribute to its development and maintenance, researchers can uncover opportunities for research translation and treatment advancement. Best practices in the field generally recommend an integration of psychotherapy, self-help groups, and pharmacological strategies delivered by trained healthcare professionals. Resources such as the Practice Guideline for the Pharmacological Treatment of Patients with Alcohol Use Disorder5 can assist healthcare professionals by providing specific statements and recommendations on evidence-based treatments for AUD.6
Although some medications have been approved for AUD (i.e., naltrexone, disulfiram, and acamprosate), pharmacological treatment remains challenging in the field. Randomized controlled trials (RCT) of these medications have shown low or moderate size effects – even when combined and compared to placebo.7 For instance, acamprosate showed advantageous effects only after complete detoxification.8 Disulfiram, which has low adherence, cannot be prescribed to patients with certain chronic clinical conditions that could worsen with alcohol ingestion.9 Other medications have been indicated as potential pharmacological agents in adjuvant therapy, including N-acetylcysteine (NAC).10
NAC, a safe medication with few adverse effects, has been used for several conditions, including paracetamol intoxication, immune deficiencies, and chronic obstructive pulmonary disease. In addition, recent evidence suggests that NAC may also have beneficial effects in a number of neuropsychiatric conditions and addictive disorders.11,12 A review concluded that although data related to NAC and addiction is still limited, the overall trend is positive for many drugs of abuse, including cannabis, methamphetamine, cocaine, nicotine, as well as gambling. NAC supplementation appears effective, affordable, safe, and tolerable.13 A double-blind, placebo-controlled RCT of outpatients with SUD receiving methadone maintenance treatment found that 12 weeks of NAC therapy had promising effects on mental health symptoms (depression and anxiety), insulin resistance, the body’s antioxidant defense system (total antioxidant capacity and reduced glutathione), and C-reactive protein levels.14
Regarding AUD, preclinical studies in rats indicate that NAC protects against neuroinflammation induced by chronic alcohol consumption 15 and decreases ethanol self-administration.16 NAC has also shown anti-relapse effects in an alcohol deprivation effect model in long-term ethanol-experienced rats.10 In humans, NAC has been associated with reduced craving symptoms in SUD17 and reduced alcohol consumption in individuals with cannabis use disorder.18 However, a recent study of individuals with AUD did not corroborate these findings, since NAC did not attenuate alcohol self-administration. Nevertheless, this study had several limitations, including a small sample size and a short intervention period.19 Studies show that drug interactions, adverse effects, limited time, and lack of consensus on the ideal NAC dosage can affect treatment efficacy and adherence.20,21
In addition to this evidence, NAC is associated with the modulation of pathophysiological processes involved in SUD, such as mitochondrial dysfunction, neuroinflammation, neurogenesis, apoptosis, and dysregulation of neurotransmitter systems.22 In this regard, NAC acts as a cysteine prodrug, helping restore central nervous system homeostasis by enhancing glutamate transporter expression and function.22 Glutamate is the main excitatory neurotransmitter of the central nervous system,23 and strong evidence has demonstrated that alcohol is involved in glutamate homeostasis impairment, mainly by interrupting its transportation.24,25
NAC is also a precursor of the amino acid glutathione, a primary endogenous antioxidant responsible for the oxidative balance of cells.12,22 Chronic administration of psychoactive substances potentiates the production of free radicals and decreases antioxidant enzymes, leading to oxidative stress.26,27 Increased lipid peroxidation and decreased antioxidant parameters during withdrawal have been observed in patients with AUD, especially early in the abstinence phase. Moreover, damage levels were related to withdrawal severity and years of dependence.28,29 NAC also has anti-inflammatory effects, which may lead to changes in peripheral biomarkers.22 Chronic alcohol use can also affect the immune system, leading to changes in inflammatory status. For instance, alterations in interleukin-6 and tumor necrosis factor alpha have been observed after acute alcohol intake and during abstinence.30
Another peripheral marker extensively assessed in individuals with SUD is brain-derived neurotrophic factor (BDNF). Although lower BDNF levels have been associated with alcohol use in individuals with AUD, its levels tend to increase during withdrawal.31 Evidence also indicates that the hypothalamic-pituitary-adrenal axis is strongly involved in SUD susceptibility, severity, and craving. Neuropeptide Y (NPY) modulates activation of the hypothalamic-pituitary-adrenal axis and has anxiolytic effects, inhibiting cortisol release.32 An association between NPY and alcohol use has been demonstrated in animal models, i.e., that it can reduce alcohol intake.33
Several studies on alcohol addiction point to changes in peripheral biomarkers, including those related to inflammatory and oxidative stress processes.28-31,34,35 Pre-clinical studies have shown that NAC has anti-inflammatory and antioxidant properties,15,16,22 suggesting improvement in biomarkers associated with the chronic addiction process and negative associated outcomes. Thus, it must be determined whether the anti-inflammatory and antioxidant effects of NAC observed in preclinical studies also occur in humans. NAC has recently been indicated as a candidate for AUD treatment.36 Considering the complexity of addictive behavior, it may be more effective to assess the potential biological effects of NAC in hospitalized patients, considering the greater control over therapy initiation and treatment adherence. The present RCT was conducted in individuals with AUD to assess the effects of NAC on treatment adherence. As secondary outcomes, the effects of NAC on clinical improvement, abstinence duration, and BDNF, NPY, oxidative stress, and inflammatory biomarker levels were investigated.
Methods
Study design and participants
This study is part of a larger RCT of individuals with AUD and/or cocaine use disorder, both diagnosed according to the DSM-5. For this specific study, we analyzed only the alcohol-related data due to the different in mechanisms of action between alcohol and cocaine. The project was registered in Clinical Trials.gov (ID NCT03018236). The total study duration was 9 weeks, including 8 weeks of adjuvant treatment intervention). Individuals were assessed every week during the study. After providing informed consent, participants were randomly allocated into a placebo or NAC group.
Individuals were recruited from the Hospital de Clínicas de Porto Alegre (HCPA) addiction unit. All patients admitted for alcohol detoxification receive a treatment protocol including oral benzodiazepines, oral folic acid 5 mg, and intravenous thiamine in doses ranging from 250 mg a day for 3 days to 500 mg 3 times a day for 5 days. The benzodiazepine dose varied as needed to alleviate withdrawal symptoms. Antidepressants were also prescribed for three patients (two in the placebo group and one in the NAC group), and antipsychotics were prescribed to seven patients (three in the placebo group and two in the NAC group).
All patients admitted to the addiction unit were screened by medical professionals and were invited to participate in the trial according to inclusion criteria: male sex, age 18-65 years, DSM-5 AUD diagnosis, and at least 7 days of current inpatient treatment. The exclusion criteria were diagnosed dependence on other substances (except tobacco), severe hepatic, renal, or cardiac conditions, a history of medical treatment for asthma or epilepsy, recent (< 14 days) or current use of medication that could interact with NAC (e.g., antiretrovirals or oral corticosteroids), a history of anaphylactic reaction to NAC, suicide risk, inability to understand or follow the research protocol, severe neuropsychiatric conditions requiring pharmacological treatment or those that could potentially interfere with the trial (e.g., dementia, schizophrenia, psychotic disorders, multiple sclerosis, severe depression, stroke, epilepsy, bipolar disorder).
A total of 700 individuals were admitted to the addiction unit between January 2017, when recruitment began, and March 2020. During the recruitment period, 73 (24.6%) of the 297 patients with AUD met all inclusion criteria. Eighteen eligible patients were discharged early or refused to participate, leaving 55 (75.3%) eligible patients who agreed to participate in the trial. Two patients were excluded during the trial due to medical conditions. Thus, the final sample consisted of 53 patients allocated into two groups (n=25 NAC, n=28 placebo) (Figure 1).

Flow diagram of the randomized, double-blind, placebo-controlled clinical trial. NAC = N-acetylcysteine.
The sample size calculation was based on studies that assessed antioxidant levels in alcohol users.37 Because a sample size of at least 30 patients with alcohol dependence (15 each in the placebo and NAC groups) would be required for an effect size of 1.093 with 80% power at a significance level (α) of 0.05, the target sample size was set to 50 patients (25 for the placebo and 25 for the NAC group), considering a sample loss of 30% during the study.
Medication intervention
The intervention consisted of NAC or placebo. The placebo drug was the same excipient used in the NAC capsule, which was composed of: 0.5% magnesium stearate, 1% colloidal silicon dioxide, 1% sodium lauryl sulfate powder, 30% pharmaceutical talc, and corn starch. The adjuvants were prescribed along with conventional therapy and were administered in capsules of similar color and shape in a double-blind fashion. The patients received oral NAC or placebo 1,200 mg/day (two 600 mg capsules/day) for up to 8 weeks (during the inpatient period, the medication was administered by trained nurses). The NAC dose was determined from previous review studies in humans on the effectiveness of NAC for neurological and psychiatric disorders, in which doses ranging from 1,200 mg to 3,600 mg per day were found safe.11,17 Patients discharged from the hospital before completing 7 days of pharmacological treatment were considered dropouts. Withdrawal was defined as an initial 7-day period of medication use (NAC or placebo) followed by: 1) refusal to continue taking the medication/placebo for any reason or 2) refusal of outpatient care after hospital discharge.
The pharmacist responsible for the HCPA inpatient unit conducted the blinding and randomization. Randomization codes were obtained using the Randomizer (www.randomizer.org/) tool. Quality control and the preparation of successive batches were applied to ensure accurate medication dosing, validity, and blinding. All batches were sent and received exclusively by the pharmacist – who dispensed the medication in bottles with no information about the medication type. The pharmacist managed all information about blinding, including the randomization codes, identification, and dates of drug dispensation for each patient. The other researchers were only unblinded after the data had been collected from both groups.
During the outpatient stage, treatment adherence was determined through a form provided to patients along with the medication (14 capsules for the week plus two capsules). Extra capsules were given to patients to ensure a consistent dose even if they experienced any issues with the pills (e.g., dropping one on the ground). In addition, all patients were instructed to record whether and when each dose was taken and record any missed doses or if any other issues occurred with the medication. The adherence to treatment outcome was also related to the number of participants who attended all study appointments.
The frequency of side effects attributable to the pharmacological intervention was assessed using the Systematic Assessment for Treatment Emergent Effects questionnaire, with similar data observed in the placebo and NAC groups (Supplementary Table S1). The Treatment Opinion Form was applied every week to ensure the blinding process. No deviation from the expected was observed for the patients or investigators (Supplementary Table S2).
Clinical assessment
Clinical and psychiatric assessments were conducted during the initial week of hospitalization using the following instruments: the sixth version of the Addiction Severity Index, the Structured Clinical Interview for DMS-IV Axis I Disorders, the Structured Clinical Interview for DMS-IV Axis II Disorders, and the Adult Self-Report Scale. Further assessments were performed at least once a week during inpatient treatment and after discharge from the addiction unit (Supplementary Figure S1). Medical evaluations, including vital signs (blood pressure and heart rate), body weight, clinical course, and addiction severity (based on Clinical Global Impression Scale results), were evaluated weekly. The intensity and frequency of craving were also assessed weekly through the Brief Substance Craving Scale. The Clinical Institute Withdrawal Assessment for Alcohol Scale was applied daily during the initial week of hospitalization, as often as necessary, and the researchers recorded each participant’s highest daily score. The Timeline Followback Questionnaire was used to assess self-reported alcohol use during the screening stage (the initial 7 days of hospitalization) and every week after hospital discharge. Breathalyzer tests were also used to verify relapse during the outpatient phase of the trial.
Biomarkers
Blood samples were collected from patients at three time points: within 24 hours of hospitalization, on the 8th day of hospitalization (at the start of pharmacological treatment), and at the end of the intervention (after 8 weeks of treatment). Blood samples were collected in tubes with and without anticoagulant and were centrifuged at 4 °C for 15 minutes at 1,500 rpm. Plasma and serum were aliquoted and frozen in microtubes at -80 °C for later analysis.
The research team performed the laboratory procedures and biological material processing at HCPA. Hepatic and renal function parameters (i.e., gamma-glutamyl transferase, alanine aminotransferase, aspartate aminotransferase, urea, and creatinine) were measured at the hospital’s Departamento de Bioquímica, Laboratório de Análises Clínicas. Oxidative stress biomarkers (i.e., glutathione peroxidase, oxidized glutathione, reduced glutathione, total glutathione, superoxide dismutase [SOD], and thiobarbituric acid reactive substances) were measured using validated commercial kits according to manufacturer instructions: Cayman Chemical Company (Ann Arbor, MI, USA) for glutathione peroxidase, SOD, and thiobarbituric acid reactive substances, and Sigma-Aldrich ( Burlington, MA, USA) for reduced glutathione, oxidized glutathione, and total glutathione. For carbonyl analysis, total protein from serum samples was quantified by the Bradford method38 and was used to normalize the samples. Carbonyl was measured as previously described.39 In brief, 1 mg of protein from each sample was normalized (serum) and transferred to sterile tubes with and without 2,4-dinitrophenylhydrazine hydrochloride. The protein was then precipitated using 20% trichloroacetic acid and centrifuged for 5 minutes at 4,000 g. The pellet was resuspended using NaOH 0.2 N, with 100 μL of HCl 2M added to samples without anticoagulant and 100 μL of DNPH 10 mM added to the samples with DNPH. The tubes were incubated for 1 hour at room temperature and, after 100 μL of trichloroacetic acid 20% was added to all tubes, they were centrifuged again for 5 minutes at 16,000 g. The pellets were then washed three times with 500 μL of ethanol: ethyl acetate (1:1) and were centrifuged again for 5 minutes at 16,000 g. The pellets were resuspended using 1 mL of urea (pH 2.3), and 200 μL were transferred to a 96-well plate to be read at 370 nm with a SpectraMaxI3 spectrophotometer.
Inflammatory biomarkers, as well as NPY and BDNF, were measured using validated commercial kits according to manufacturer instructions. Interleukin-6-1β, -2, -6, -10, and tumor necrosis factor alpha were assessed using the ProcartaPlex™ Multiplex Bead Immunoassay (Thermo Fisher Scientific/Invitrogen by Life Technologies, Vienna, Austria), while NPY and BDNF were measured using enzyme-linked immunosorbent assay kits (Merck, Darmstadt, Germany). Although NPY and inflammatory biomarker measurement were not specified in the registered protocol, they were included in the study at the beginning of the intervention to determine how NAC affected them, for comparison with the literature.
Statistical analyses
The collected patient data were entered into REDCap and exported to IBM SPSS Statistics 18 for analysis. All analyses were performed on an intention-to-treat basis, i.e., all data were analyzed according to initially allocated patient groups, regardless of treatment adherence or withdrawal from the study. Categorical variables are presented as absolute frequency and percentage, while continuous variables with asymmetric distribution are presented as median and interquartile ranges (25-75).
First, data were compared between the NAC and placebo groups, as described below. Sociodemographic, clinical, and psychiatric data were compared between the NAC and placebo groups using the chi-square and Mann-Whitney U tests. The frequency of side effects, the intensity and frequency of craving, and the severity of clinical impression were compared between groups using the chi-square test. Next, data related to duration of study participation and treatment adherence were evaluated. Duration of study participation was assessed through the Mann-Whitney U test, whereas treatment adherence and time until relapse were assessed using the chi-square test and Kaplan-Meier analysis. Spearman correlations were applied to assess the relationship between biological markers and duration of study participation.
To explore the effects of NAC and time on the included peripheral biomarkers, generalized estimating equation models were used. These models assessed the main effects of intervention type (NAC vs. placebo) and time (week 0 [W0], W1, and W8), as well as the interaction between these factors, on all biological markers (hepatic and renal function parameters, BDNF, NPY, and inflammatory and oxidative stress biomarkers). Linear distribution and robust estimation with an unstructured working correlation matrix were used. A Bonferroni post-hoc test was used to adjust the significance level of the tested multiple contrasts. The significance level for all tests was 0.05.
Ethics statement
This study was approved by the HCPA Research Ethics Committee (number 15-0488; CAAE/CONEP-Brazil: 50057815.7.0000.5327) and followed Declaration of Helsinki guidelines. All participants provided written informed consent prior to enrollment.
Results
The NAC and placebo groups had similar sociodemographic characteristics and psychiatric comorbidity prevalences (Table 1). Individuals were predominantly single, White, and employed, with a median age of 52 years and a low education level (p > 0.05). Body mass index values were generally within the normal range. Most patients had mild or moderate alcohol withdrawal symptoms during the initial week of hospitalization, as indicated by Clinical Institute Withdrawal Assessment for Alcohol Scale scores,40 and reported previous addiction treatment. However, the number of hospitalizations did not differ between the groups. The participants reported a long history of alcohol consumption, with a median duration of 20 to 25 years. In the 30 days prior to hospitalization, they consumed alcohol nearly every daily. AUD severity, as determined by the Addiction Severity Index, was similar between the groups. The intensity and frequency of craving were similar between groups throughout the trial, except during the initial week of intervention, with the NAC group reporting greater craving (intensity, 34.8%; frequency, 39.1%) than the placebo group (intensity, p = 0.002; frequency, p = 0.001) (Supplementary Table S3).
Sociodemographic data, psychiatric comorbidities, personality disorder, and substance use profile in patients with alcohol use disorder (n=53†)
Treatment adherence was similar between groups (p > 0.05) (Table 2). Most individuals (61% in the placebo group and 64% in the NAC group) completed the research protocol without relapse, dropout, or withdrawal. No significant differences in mean time until relapse were found between the groups: 51.5 days (95%CI 44.1-58.9) in the placebo group, and 54.4 (95%CI 47.1-61.6) in the NAC group (p = 0.769) (Supplementary Figure S2). Six patients (placebo, n=4; NAC, n=2) dropped out of the study during the initial week of the intervention. Duration of study participation was not associated with age, race, marital status, employment status, education level, years of alcohol use, use in the last 30 days, or severity of dependence in either intervention group (p > 0.05).
Duration of study participation and treatment adherence in patients with alcohol use disorder (n = 53)
Intervention group was not associated with duration (in days) of study participation, length of hospital stay, or outpatient follow-up (p > 0.05) (Table 2). Most patients (85% to 95%) adequately adhered to the medication regimen during the initial phase of the study, with no significant difference between the groups. However, adherence decreased, especially during the outpatient phase. About 20%-25% of the patients reported missing one pill a week, and about 8%-15% reported missing ≥ 2 pills a week.
According to the Clinical Global Impression results, the condition of > 55% of patients in both groups was moderate or severe at the start of the study (W0) (Supplementary Figure S3 and Supplementary Table S4). However, Clinical Global Impression scores improved throughout the study in both groups, especially between W0 and W1 (ppairwise < 0.001).
Biomarker analysis revealed significant changes over time in all hepatic and renal function parameters (Figure 2, Supplementary Table S5). Gamma-glutamyl transferase, aspartate aminotransferase, and alanine aminotransferase levels decreased similarly over time in both groups, with a significant difference in W8 compared to admission (W0) and W1 (placebo group – gamma-glutamyl transferase pglobal < 0.001, aspartate aminotransferase pglobal < 0.001, alanine aminotransferase pglobal = 0.015; NAC group – gamma-glutamyl transferase pglobal = 0.001, aspartate aminotransferase pglobal < 0.001, alanine aminotransferase pglobal = 0.002).

Longitudinal analysis of hepatic parameters in patients with alcohol use disorder according to intervention type. Data presented as mean and standard error. ALT = alanine aminotransferase; AST = aspartate aminotransferase; GGT = gamma-glutamyl transferase; NAC = N-acetylcysteine. * p < 0.05 for pairwise comparisons.
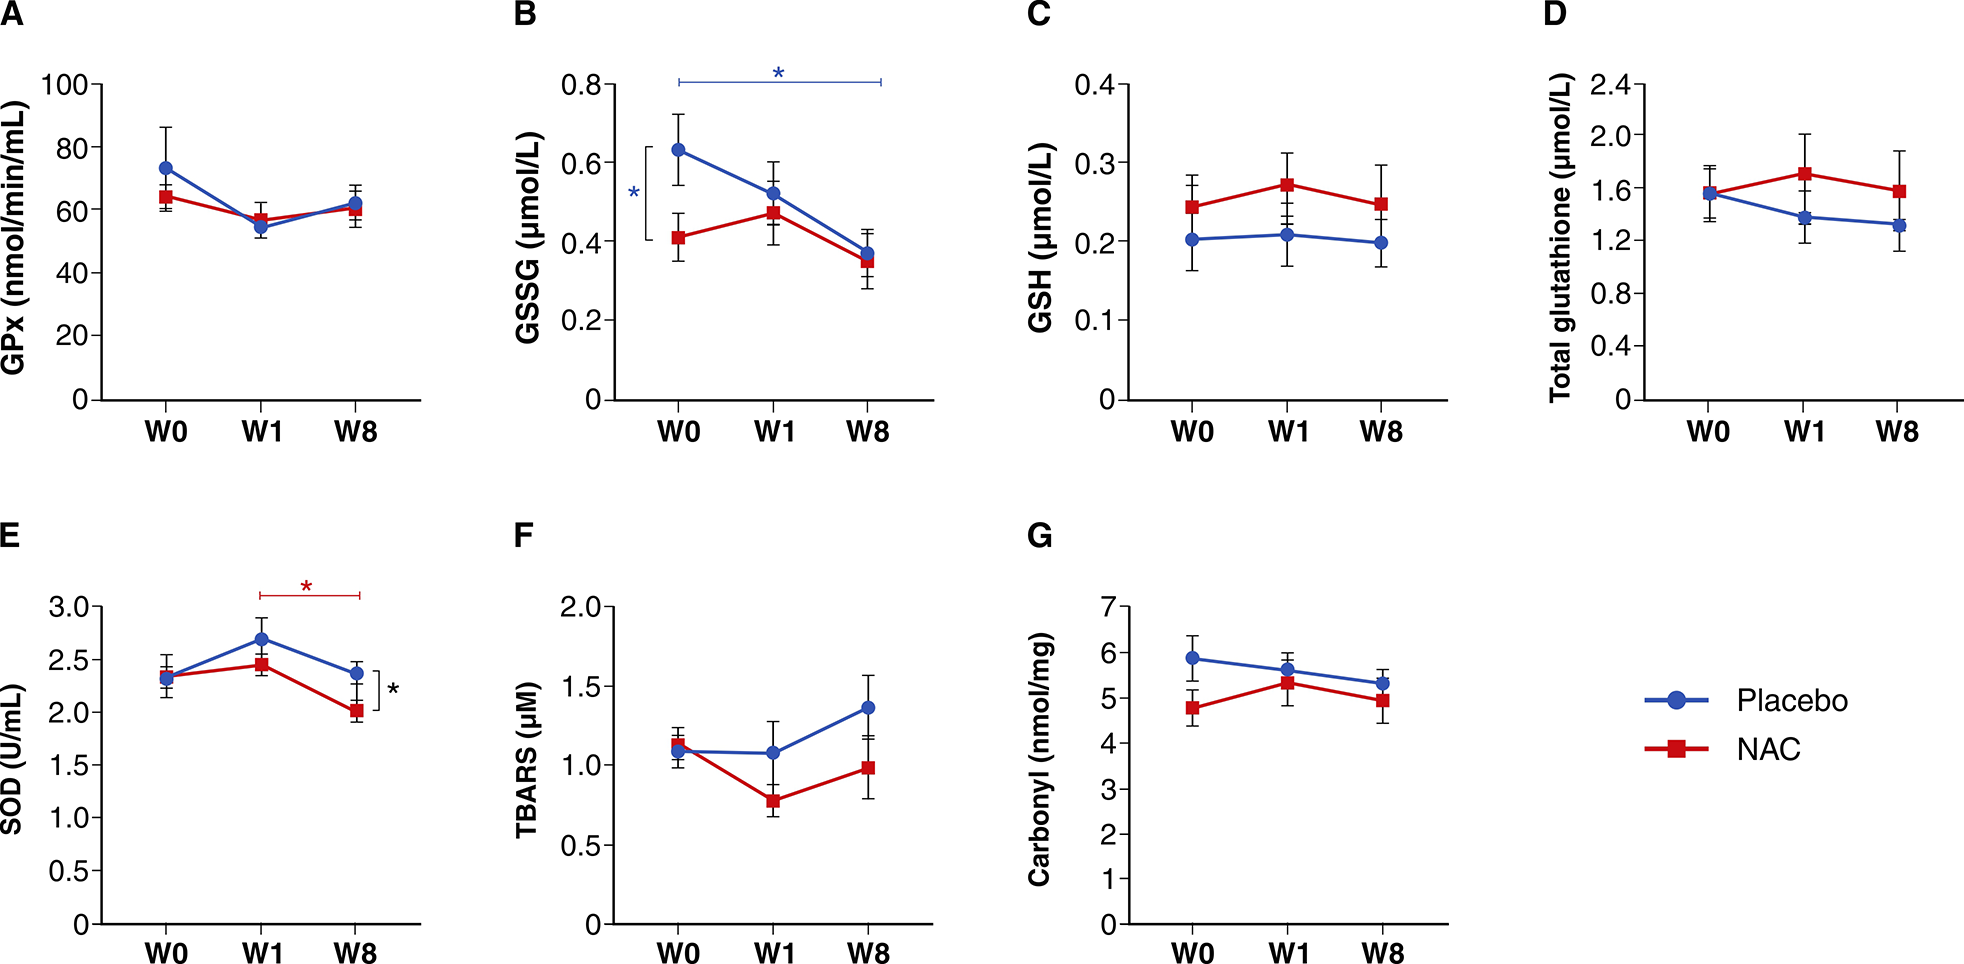
Figure 3 and Supplementary Table S5 show the results of the oxidative stress marker analysis. Oxidized glutathione levels at admission (W0) were lower in the NAC group than the placebo group (ppairwise = 0.043). At the end of the study (W8), both groups presented similar oxidized glutathione levels (p = 0.868), despite a decrease in in the placebo group, especially between admission (W0) and the end of the study (W8, ppairwise = 0.014). No change was detected in the NAC group (pglobal = 0.359). Moreover, SOD activity had decreased by the end of the intervention in the NAC group (W1 to W8, ppairwise < 0.001) and was lower than the placebo group (ppairwise = 0.009).

Longitudinal analysis of oxidative stress biomarkers in patients with alcohol use disorder according to intervention type. The data are presented as mean and standard error. GPx = glutathione peroxidase; GSH = reduced glutathione; GSSG = oxidized glutathione; SOD = superoxide dismutase; TBARS = thiobarbituric acid reactive substances. * p < 0.05 for pairwise comparisons.
NPY levels also changed over time in the NAC group (pglobal = 0.001), increasing by the end of the study (W8) compared to admission (W0, ppairwise = 0.050) and W1 (ppairwise = 0.001). Inflammatory biomarkers and BDNF levels did not change significantly during the trial and did not differ between the groups (Figure 4 and Supplementary Table S5).
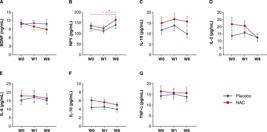
Longitudinal analysis of BDNF, NPY, and inflammatory biomarkers in patients with alcohol use disorder according to intervention type. The data are presented as mean and standard error. BDNF = brain-derived neurotrophic factor; IL = interleukin; NPY = neuropeptide Y; TNF = tumor necrosis factor. * p < 0.05 for pairwise comparisons.
Additional analyses investigated whether these biomarkers were correlated with duration of study participation (days). No correlation was observed in the placebo group, while two associations were observed in the NAC group. Reduced glutathione levels at admission (W0) were positively correlated with duration of participation (r = 0.433, p = 0.039). However, carbonyl levels at W0 were negatively correlated with this outcome (r = -0.519, p = 0.009).
Discussion
This is the first double-blind RCT to investigate the effect of NAC as an adjuvant treatment for detoxification in individuals with AUD while admitted to a public hospital. There were no significant differences in treatment adherence, clinical improvement, or abstinence duration between the NAC and placebo groups. During the initial week of hospitalization (prior to the intervention), there was significant clinical improvement in all patients. To expand the outcomes commonly evaluated in RCTs, which usually involve clinical features related to addiction, we investigated several peripheral biomarkers to examine the impact of NAC therapy. Our results showed some differences in oxidative stress markers between the groups, especially after 8 weeks of intervention. Furthermore, NPY levels significantly increased at the end of the study in the NAC group. Changes in renal and hepatic parameters were also observed in both groups. However, NAC had no effect on BDNF or inflammatory markers.
Evidence suggests that NAC can alter peripheral biomarkers in alcohol users. Renal and hepatic enzymes are usually increased in individuals with AUD and tend to normalize during abstinence.41 Gamma-glutamyl transferase and transaminases levels were reduced after 8 weeks of intervention (W8), which indicates that including NAC in baseline treatment had neither a positive nor a negative effect on these biomarkers. Furthermore, NPY levels increased during the trial, especially in the NAC group. As far as we know, no RCT has assessed NPY levels in association with NAC therapy. In addition, very few studies have evaluated individuals with AUD; most have used animal models. One study indicated that after administering NPY in the brain of rats with ethanol abstinence, alcohol intake decreased.33 Similarly, acute and chronic alcohol intake can decrease NPY expression in specific brain regions, such as the amygdala, hypothalamus, and parietal cortex.42 Considering the close relationship between NPY and the hypothalamic-pituitary-adrenal axis, these findings also suggest that NPY levels might increase during alcohol abstinence to modulate and regulate the hypothalamic-pituitary-adrenal axis, which aligns with our results.
Changes in certain oxidative stress biomarkers were also observed. Alcohol metabolism is related to the production of reactive oxygen species, increasing the risk of oxidative stress.35 The NAC group had lower SOD levels than the placebo group at the end of the intervention, which is relevant since SOD is an important antioxidant defense. Other studies have had similar findings during alcohol detoxification.34 Nevertheless, no RCT with NAC as an intervention has evaluated oxidative markers in AUD. We hypothesized that decreased SOD would not interfere with the short-term clinical parameters measured in this trial, although it may affect the neuroprogression of AUD and the course of the disorder.35 Moreover, there was a reduction in oxidized glutathione levels in the placebo group. Lower oxidized glutathione levels suggest an imbalance in the regulation of glutathione metabolism, which indicates reduced inactivation of reactive oxygen species and impaired antioxidant defense.43 Although these unexpected effects require further investigation, they also reinforce the effects of alcohol on oxidative stress, even during early withdrawal.
Two correlations with duration of study participation were observed, both in the NAC group. Higher baseline (W0) levels of reduced glutathione were correlated with longer participation. Although chronic alcohol use has been associated with lower reduced glutathione levels in previous studies,44 our results suggest that the concentration of this biomarker varies significantly in individuals with AUD. Higher levels of this biomarker may indicate greater susceptibility and adherence to detoxification treatment. In addition, lower carbonyl levels at admission (W0) were correlated with longer study participation. Previous studies indicate that higher carbonyl levels are associated with alcohol addiction.45 As in the above mentioned scenario, the substantial variability observed in these peripheral biomarkers could assist in the search for biomarkers related to alcohol use and treatment adherence.
Although NAC had no observable influence on addiction-related clinical outcomes in our trial, previous studies have suggested that it has a beneficial impact on SUD. In a meta-analysis of seven studies, Duailibi et al.17 found that NAC was significantly better than placebo at reducing craving in patients with SUD. Therefore, NAC has been indicated as a pharmacological agent of interest due to its low cost and limited adverse effects. However, studies reporting improved AUD treatment outcomes with NAC have mostly involved animal models, other substances of abuse, or a different, less restricted design than double-blind RCT.46 Furthermore, our sample consisted of inpatients with severe addiction disorder who used alcohol but no other substances except nicotine.
A recent review suggested that NAC only adds a small benefit to usual SUD treatment, showing limited clinical efficacy.46 However, several registered clinical trials are currently assessing the effects of NAC, whether combined with other interventions or not, on AUD. Preliminary findings also indicate that NAC has no additional effects on treatment.35 Although other studies, including RCTs, have investigated whether NAC is a useful pharmacological agent in addiction treatment for substances other than alcohol, most observed no improvement in clinical features. NAC has no effect on methamphetamine use or the severity of craving, dependence, or withdrawal compared to placebo.47 In a double-blind placebo-controlled trial of NAC for cocaine dependence, LaRowe et al.48 found no evidence of efficacy in patients who were not in the abstinence phase. Similarly, another trial found no evidence that NAC was efficacious in adults with cannabis use disorder.49 None of these studies exclusively included patients with AUD. One curious RCT compared the effects of NAC and placebo on hangover symptoms,50 again finding no evidence that NAC contributed to overall clinical improvement regarding excessive alcohol use.
New pharmacological treatments should only be prescribed if their benefits are confirmed in rigorous studies. Although treatment adherence and abstinence are key outcomes for clinical improvement in SUD, investigating the effects of new pharmacological treatments on peripheral biomarkers might help clarify the complexity of addiction and response. Current pharmacological treatment for AUD only has modest effects, and relapse is common.51-53 Therefore, well-conducted RCTs are imperative, especially when a pharmacological agent formerly indicated as a treatment alternative has shown no impact on clinical improvement.
This study has some limitations. Participants were selected by convenience and consecutively. Therefore, all eligible patients admitted to the addiction unit were invited to participate. This could have led to bias and intrinsic differences between the NAC and placebo groups. Nevertheless, the sociodemographic and clinical characteristics were very similar between the groups. Moreover, since we did not evaluate the effect of NAC on biological and clinical outcomes during alcohol misuse, our results should not be extrapolated to active alcohol users. Our inclusion criteria allowed for patients who did not receive outpatient treatment at the HCPA unit, which could have increased follow-up losses. However, this may also have been an advantage when evaluating medication efficacy, since compliance was assured during the initial weeks. The use of self-report and retrospective questionnaires may have yielded some biased data due to social desirability and memory issues. Furthermore, because our sample size was relatively small for determining differences in clinical outcomes, a beta error may have resulted. Regarding medication bias, it should be pointed out that all patients admitted for alcohol detoxification receive a standard treatment protocol, including benzodiazepines and/or B vitamins. To our knowledge, no studies have shown that these medications interfere with the effectiveness of NAC. Patients using medications that could interfere with NAC, such as antiretrovirals, and corticosteroids were excluded, as mentioned in the methods section. The fact that we did not analyze the interference of other possible medications for psychiatric comorbidities, such as antipsychotics, antidepressants, and mood modulators, could be considered a limitation since it may have influenced biochemical parameters. However, the prevalence of psychiatric comorbidities and the use of such medications were similar in both groups. Furthermore, considering that a significant proportion of psychoactive substance users have comorbid psychiatric disorders, the groups reflect the real-world patient profile.
In summary, some peripheral biomarkers, including hepatic and renal parameters and NPY levels, improved during the trial, despite the short period of abstinence. However, the reduction in SOD levels in the intervention group could indicate that NAC is harmful. Thus, caution is necessary when analyzing the benefits of a new drug without knowing its long-term consequences. Moreover, NAC did not improve clinical outcomes, such as treatment adherence or abstinence duration, compared to placebo in this rigorously designed double-blind RCT. The lack of effect on clinical parameters is in line with previous studies of NAC as an intervention for other addiction disorders. Finally, future RCTs involving large samples, outpatients with less severe AUD, and longer follow-up may be needed to determine whether NAC improves inflammatory parameters and treatment outcomes and reduces the clinical and mental health burden of this chronic disorder.
Acknowledgements
This study was supported by the Secretaria Nacional de Políticas Sobre Drogas (grant 08129.011787/2015-95), Fundo de Incentivo à Pesquisa e Eventos, Hospital de Clínicas de Porto Alegre (grant 2015-0488), and Coordenação de Aperfeiçoamento de Pessoal de Nível Superior (Finance Code 001).
References
- 1 American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5). Arlington: American Psychiatric Publishing;2013.
- 2 Rehm J, Shield KD. Global burden of disease and the impact of mental and addictive disorders. Curr Psychiatry Rep. 2019;21:10.
- 3 Murray CJ. Quantifying the burden of disease: the technical basis for disability-adjusted life years. Bull World Health Organ. 1994;72:429-45.
- 4 Vos T, Lim SS, Abbafati C, Abbas KM, Abbasi M, Abbasifard M, et al. Global burden of 369 diseases and injuries in 204 countries and territories, 1990-2019: a systematic analysis for the Global Burden of Disease Study 2019. Lancet. 2020;396:1204-22.
- 5 Reus VI, Fochtmann LJ, Bukstein O, Eyler AE, Hilty DM, Horvitz-Lennon M, et al. The American Psychiatric Association Practice Guideline for the Pharmacological Treatment of Patients With Alcohol Use Disorder. Am J Psychiatry. 2018;175:86-90.
- 6 Donato S, Ray L. Neurobiology and the Treatment of Alcohol Use Disorder: A Review of the Evidence Base. Subst Abuse Rehabil. 2023;14:157-66.
- 7 Kranzler HR, Soyka M. Diagnosis and Pharmacotherapy of Alcohol Use Disorder. JAMA. 2018;320:815.
- 8 Kampman KM, Pettinati HM, Lynch KG, Xie H, Dackis C, Oslin DW, et al. Initiating acamprosate within-detoxification versus post-detoxification in the treatment of alcohol dependence. Addict Behav. 2009;34:581-6.
- 9 Mutschler J, Grosshans M, Soyka M, Rösner S. Current Findings and Mechanisms of Action of Disulfiram in the Treatment of Alcohol Dependence. Pharmacopsychiatry. 2016;49:137-41.
- 10 Cano‐Cebrián MJ, Fernández‐Rodríguez S, Hipólito L, Granero L, Polache A, Zornoza T. Efficacy of N‐acetylcysteine in the prevention of alcohol relapse‐like drinking: Study in long‐term ethanol‐experienced male rats. J Neurosci Res. 2021;99:638-48.
- 11 Deepmala, Slattery J, Kumar N, Delhey L, Berk M, Dean O, et al. Clinical trials of N-acetylcysteine in psychiatry and neurology: A systematic review. Neurosci Biobehav Rev. 2015;55:294-321.
- 12 Minarini A, Ferrari S, Galletti M, Giambalvo N, Perrone D, Rioli G, et al. N-acetylcysteine in the treatment of psychiatric disorders: current status and future prospects. Expert Opin Drug Metab Toxicol. 2017;13:279-92.
- 13 Ghaderi A, Vahed N, Ghayoomi R, Ostadmohammadi V, Gholami M, Dehkohneh S. N-acetylcysteine in addiction management: current knowledge and future perspectives. Int J Pharm Res. 2019;11:13.
- 14 Padoei F, Mamsharifi P, Hazegh P, Boroumand H, Ostadmohammady F, Abbaszadeh‐Mashkani S, et al. The therapeutic effect of N‐acetylcysteine as an add‐on to methadone maintenance therapy medication in outpatients with substance use disorders: a randomized, double‐blind, placebo‐controlled clinical trial. Brain Behav. 2023;13:e2823.
- 15 Schneider R, Bandiera S, Souza DG, Bellaver B, Caletti G, Quincozes-Santos A, et al. N-acetylcysteine Prevents Alcohol Related Neuroinflammation in Rats. Neurochem Res. 2017;42:2135-41.
- 16 Lebourgeois S, González-Marín MC, Antol J, Naassila M, Vilpoux C. Evaluation of N-acetylcysteine on ethanol self-administration in ethanol-dependent rats. Neuropharmacology. 2019;150:112-20.
- 17 Duailibi MS, Cordeiro Q, Brietzke E, Ribeiro M, LaRowe S, Berk M, et al. N-acetylcysteine in the treatment of craving in substance use disorders: Systematic review and meta-analysis. Am J Addict. 2017;26:660-6.
- 18 Squeglia LM, Tomko RL, Baker NL, McClure EA, Book GA, Gray KM. The effect of N-acetylcysteine on alcohol use during a cannabis cessation trial. Drug Alcohol Depend. 2018;185:17-22.
- 19 Stoops WW, Strickland JC, Hays LR, Rayapati AO, Lile JA, Rush CR. Influence of n-acetylcysteine maintenance on the pharmacodynamic effects of oral ethanol. Pharmacol Biochem Behav. 2020;198:173037.
- 20 Dean O, Giorlando F, Berk M. N-acetylcysteine in psychiatry: current therapeutic evidence and potential mechanisms of action. J Psychiatry Neurosci. 2011;36:78-86.
- 21 Samuni Y, Goldstein S, Dean OM, Berk M. The chemistry and biological activities of N-acetylcysteine. Biochim Biophys Acta Gen Subj. 2013;1830:4117-29.
- 22 Bradlow RCJ, Berk M, Kalivas PW, Back SE, Kanaan RA. The potential of N-Acetyl-L-Cysteine (NAC) in the treatment of psychiatric disorders. CNS Drugs. 2022:36:451-82.
- 23 Brosnan JT, Brosnan ME. Glutamate: a truly functional amino acid. Amino Acids. 2013;45:413-8.
- 24 Bell RL, Hauser SR, McClintick J, Rahman S, Edenberg HJ, Szumlinski KK, et al. Ethanol-associated changes in glutamate reward neurocircuitry: a minireview of clinical and preclinical genetic findings. Prog Mol Biol Transl Sci. 2016;137:41-85.
- 25 Burnett EJ, Chandler LJ, Trantham-Davidson H. Glutamatergic plasticity and alcohol dependence-induced alterations in reward, affect and cognition. Prog Neuropsychopharmacol Biol Psychiatry. 2016;65:309-20.
- 26 Uys JD, Mulholland PJ, Townsend DM. Glutathione and redox signaling in substance abuse. Biomed Pharmacother. 2014;68:799-807.
- 27 Tan HK, Yates E, Lilly K, Dhanda AD. Oxidative stress in alcohol-related liver disease. World J Hepatol. 2020;12:332-49.
- 28 Huang M-C, Chen C-C, Pan C-H, Chen C-H. Comparison of oxidative DNA damage between alcohol-dependent patients with and without delirium tremens. Alcohol Clin Exp Res. 2014;38:2523-8.
- 29 Saribal D, Hocaoglu-Emre FS, Karaman F, Mırsal H, Akyolcu MC. Trace element levels and oxidant/antioxidant status in patients with alcohol abuse. Biol Trace Elem Res. 2020;193:7-13.
- 30 Heberlein A, Käser M, Lichtinghagen R, Rhein M, Lenz B, Kornhuber J, et al. TNF-α and IL-6 serum levels: neurobiological markers of alcohol consumption in alcohol-dependent patients? Alcohol. 2014;48:671-6.
- 31 Valerio AG, Ornell F, Roglio VS, Scherer JN, Schuch JB, Bristot G, et al. Increase in serum brain-derived neurotrophic factor levels during early withdrawal in severe alcohol users. Trends Psychiatry Psychother. 2022:44:e20210254.
- 32 Antonijevic IA, Murck H, Bohlhalter S, Frieboes RM, Holsboer F, Steiger A. Neuropeptide Y promotes sleep and inhibits ACTH and cortisol release in young men. Neuropharmacology. 2000;39:1474-81.
- 33 Gilpin NW, Stewart RB, Badia-Elder NE. Neuropeptide Y suppresses ethanol drinking in ethanol-abstinent, but not non-ethanol-abstinent, Wistar rats. Alcohol. 2008;42:541-51.
- 34 Dries SS, Seibert BS, Bastiani MF, Linden R, Perassolo MS. Evaluation of oxidative stress biomarkers and liver and renal functional parameters in patients during treatment in a mental health unit to treat alcohol dependence. Drug Chem Toxicol. 2022;45:861-7.
- 35 Tsermpini EE, Plemenitaš Ilješ A, Dolžan V. Alcohol-induced oxidative stress and the role of antioxidants in alcohol use disorder: a systematic review. Antioxidants. 2022;11:1374.
- 36 Aubin HJ. Repurposing drugs for treatment of alcohol use disorder. Int Rev Neurobiol. 2024:175:153-185.
- 37 Wu Y, Pan X, Zhang S, Wang W, Cai M, Li Y, et al. Protective effect of corn peptides against alcoholic liver injury in men with chronic alcohol consumption: a randomized double-blind placebo-controlled study. Lipids Health Dis. 2014;13:192.
- 38 Bradford M. A rapid and sensitive method for the quantitation of microgram quantities of protein utilizing the principle of protein-dye binding. Anal Biochem. 1976;72:248-54.
- 39 Levine RL, Garland D, Oliver CN, Amici A, Climent I, Lenz AG, et al. Determination of carbonyl content in oxidatively modified proteins. Methods Enzymol. 1990. p. 464-78.
- 40 Sullivan JT, Sykora K, Schneiderman J, Naranjo CA, Sellers EM. Assessment of alcohol withdrawal: the revised Clinical Institute Withdrawal Assessment for Alcohol Scale (CIWA-Ar). Br J Addict. 1989;84:1353-7.
- 41 Rosoff DB, Charlet K, Jung J, Lee J, Muench C, Luo A, et al. Association of high-intensity binge drinking with lipid and liver function enzyme levels. JAMA Netw Open. 2019;2:e195844.
- 42 Roy A, Pandey SC. The decreased cellular expression of neuropeptide Y protein in rat brain structures during ethanol withdrawal after chronic ethanol exposure. Alcohol Clin Exp Res. 2002;26:796-803.
- 43 Nur E, Verwijs M, de Waart DR, Schnog J-JB, Otten HM, Brandjes DP, et al. Increased efflux of oxidized glutathione (GSSG) causes glutathione depletion and potentially diminishes antioxidant defense in sickle erythrocytes. Biochim Biophys Acta Mol Basis Dis. 2011;1812:1412-7.
- 44 Uys JD, Mulholland PJ, Townsend DM. Glutathione and redox signaling in substance abuse. Biomed Pharmacother. 2014;68:799-807.
- 45 Kapaki E, Liappas I, Lyras L, Paraskevas GP, Mamali I, Theotoka I, et al. Oxidative damage to plasma proteins in patients with chronic alcohol dependence: the effect of smoking. In Vivo (Brooklyn). 2007;21:523.
- 46 Smaga I, Frankowska M, Filip M. N-acetylcysteine in substance use disorder: a lesson from preclinical and clinical research. Pharmacol Rep. 2021;73:1205-19.
- 47 McKetin R, Dean OM, Turner A, Kelly PJ, Quinn B, Lubman DI, et al. N-acetylcysteine (NAC) for methamphetamine dependence: a randomised controlled trial. EClinicalMedicine. 2021;38:101005.
- 48 LaRowe SD, Kalivas PW, Nicholas JS, Randall PK, Mardikian PN, Malcolm RJ. A double-blind placebo-controlled trial of N-acetylcysteine in the treatment of cocaine dependence. Am J Addict. 2013;22:443-52.
- 49 Gray KM, Sonne SC, McClure EA, Ghitza UE, Matthews AG, McRae-Clark AL, et al. A randomized placebo-controlled trial of N-acetylcysteine for cannabis use disorder in adults. Drug Alcohol Depend. 2017;177:249-57.
- 50 Coppersmith V, Hudgins S, Stoltzfus J, Stankewicz H. The use of N-acetylcysteine in the prevention of hangover: a randomized trial. Sci Rep. 2021;11:13397.
- 51 Cheng HY, McGuinness LA, Elbers RG, MacArthur GJ, Taylor A, McAleenan A, et al. Treatment interventions to maintain abstinence from alcohol in primary care: systematic review and network meta-analysis. BMJ. 2020;m3934.
- 52 Volkow ND, Boyle M. Neuroscience of addiction: relevance to prevention and treatment. Am J Psychiatry. 2018;175:729-40.
- 53 Soyka M, Mutschler J. Treatment-refractory substance use disorder: focus on alcohol, opioids, and cocaine. Prog Neuropsychopharmacol Biol Psychiatry. 2016;70:148-61.